The all-oral treatment is approved for certain adults with advanced or metastatic breast cancer after endocrine therapy stops working.
The U.S. Food and Drug Administration has approved a new combination treatment for some people with advanced or metastatic breast cancer whose tumors carry a specific genetic change known as an ESR1 mutation.
The Sept. 18 approval covers imlunestrant (Inluriyo) combined with abemaciclib (Verzenio) for adults with estrogen receptor-positive, HER2-negative, ESR1-mutated breast cancer whose disease has progressed after at least one line of endocrine therapy. Both drugs are manufactured by Eli Lilly.
For patients and families, the significance goes beyond the new drug combination itself. The approval also highlights the growing role of molecular testing in deciding which treatment may be appropriate for a particular cancer.
What is an ESR1 mutation?
ESR1 is the gene that provides instructions for the estrogen receptor. Some breast cancers depend on estrogen signals to grow.
An ESR1 mutation can develop during treatment and may contribute to resistance to some endocrine therapies. That makes identifying the mutation potentially important when cancer progresses.
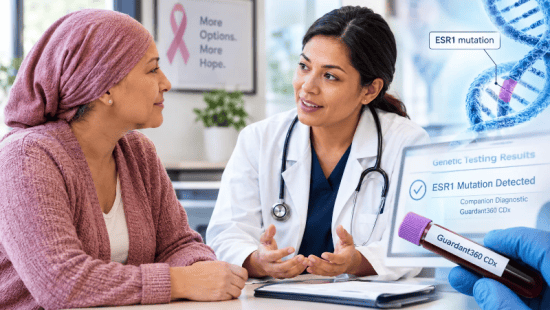
The FDA approved Guardant360 CDx, a blood-based companion diagnostic, to identify specific ESR1 mutations in patients who may be eligible for the Inluriyo-Verzenio combination. The FDA says ESR1 status in the EMBER-3 trial was determined through circulating tumor DNA in blood.
That means treatment decisions can increasingly depend not only on the type and stage of breast cancer, but also on what molecular changes are found in the tumor.
We have reported before on the importance of making complex health information easier for patients and families to understand, including how medical language can create barriers for Latino communities.
The approval was based on the Phase 3 EMBER-3 trial, which enrolled 874 adults with ER-positive, HER2-negative locally advanced or metastatic breast cancer who had previously received an aromatase inhibitor, either alone or with a CDK4/6 inhibitor.
Among the 159 patients whose tumors carried an ESR1 mutation, researchers compared Inluriyo plus Verzenio with Inluriyo alone.
The results:
- 11.1 months: median progression-free survival with the combination
- 5.5 months: median progression-free survival with Inluriyo alone
- 35%: objective response rate with the combination
- 15%: objective response rate with Inluriyo alone
The FDA reported a hazard ratio of 0.53 for progression-free survival in this ESR1-mutated subgroup.
In plain English, patients receiving the combination went a median of about 11 months before their cancer progressed or they died, compared with about 5.5 months among those receiving Inluriyo alone.
But there is an important distinction: this was progression-free survival, not overall survival. The FDA said overall-survival data were still immature at the interim analysis.
So the approval does not mean the treatment has been shown to double how long patients live.
What are the side effects?
The fact that both medicines are taken by mouth does not mean treatment is free of significant side effects or monitoring.
Abemaciclib’s FDA warnings and precautions include diarrhea, neutropenia, interstitial lung disease or pneumonitis, liver toxicity, blood clots and embryo-fetal toxicity. Imlunestrant also carries a warning concerning embryo-fetal toxicity.
In clinical-trial data for the combination, diarrhea was particularly common. Other reported adverse reactions included nausea, fatigue, vomiting, abdominal pain, infections and decreased appetite.
Blood tests can also show changes in blood-cell counts and liver and metabolic measurements.
Patients should therefore discuss expected side effects and monitoring with their oncology team before beginning treatment.
Who might qualify?
The FDA approval is specific. It is for adults whose cancer is:
- ER-positive
- HER2-negative
- ESR1-mutated
- Advanced or metastatic
- Progressing after at least one line of endocrine therapy
- Confirmed to have the relevant ESR1 mutation with an FDA-authorized test.
It is not a treatment for all breast cancers.
It also does not mean that everyone with ER-positive breast cancer has an ESR1 mutation.
What should patients ask their doctor?
For someone whose advanced breast cancer has progressed after endocrine therapy, the new approval may make molecular testing an important part of the treatment conversation.
Questions to ask an oncology team include:
- Has my cancer been tested for an ESR1 mutation?
- What test was used?
- Does my cancer meet the FDA-approved criteria for this combination?
- What are the potential benefits compared with other available treatments?
- What side effects should I watch for?
- What blood tests or other monitoring will I need?
- How might my insurance affect access to the treatment or testing?
For patients already navigating the cost and complexity of cancer care, questions about access matter as much as questions about the medicine itself. Parriva has also reported on healthcare access challenges affecting Latino Californians and the financial pressure healthcare costs can place on California Latino households.
The bigger change: treatment is becoming more personalized
The FDA’s approval illustrates a broader shift in cancer treatment: the name of the cancer is only part of the treatment decision.
Doctors may also look at specific genetic or molecular characteristics of a tumor to determine which therapies are appropriate.
For patients with ESR1-mutated, ER-positive, HER2-negative advanced breast cancer, the Inluriyo-Verzenio approval adds another FDA-approved treatment option after progression on endocrine therapy.
For patients and families, the practical question is no longer simply, “What treatment is available for breast cancer?”
It is increasingly:
“What does my cancer’s biology tell us about which treatment may be appropriate for me?”
This article is for general information and is not a substitute for medical advice. Treatment decisions should be made with a qualified oncology team.